Foam Rolling: The Complete Guide to What It Does and What It Does Not
Quick Answer: Foam rolling reliably produces short-term increases in range of motion without reducing strength, and it modestly reduces perceived muscle soreness. It does not break up scar tissue, lengthen fascia, or release adhesions, and it does not meaningfully improve long-term flexibility on its own. Use it before training to improve range without a warm-up cost, and after training or on rest days for soreness, and use stretching and strength work for lasting change.
The research on this is better than it was ten years ago, and it points somewhere specific: a genuinely useful tool, doing something other than what the original explanation claimed.


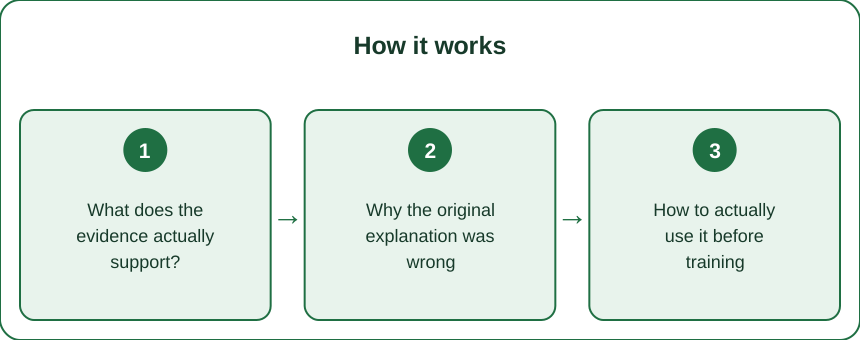
What does the evidence actually support?
Two effects hold up reasonably consistently, and it is worth being precise about their size and duration.
Short-term range of motion improvement. Rolling a muscle group for somewhere between 30 and 120 seconds reliably increases joint range of motion measured immediately afterward. The effect size is meaningful and it appears across many studies.
Critically, this happens without the acute strength or power reduction that prolonged static stretching can produce. That combination, more range without a performance cost, is the strongest practical argument for including it in a warm-up, and it is why foam rolling largely displaced long static stretching before training.
The duration of the effect is limited. Most studies find it lasting somewhere in the range of ten to thirty minutes, which means it is a preparation tool rather than a flexibility intervention.
Reduced perceived soreness. Rolling after training, or in the days following hard training, modestly reduces the subjective experience of delayed onset muscle soreness and can slightly improve performance measures during that recovery window. The effect is real and it is moderate rather than dramatic.
What the evidence does not strongly support: long-term flexibility gains from rolling alone, injury prevention, meaningful changes in muscle tissue structure, improvements in blood flow that translate to faster recovery, and effects on cellulite or fat.
The honest summary is a tool with two solid, moderate, short-duration benefits. That is genuinely worth ten minutes of your week. It is not worth the claims made for it in most marketing.
Why the original explanation was wrong
The mechanism matters because it changes how you should use the tool, and the original story was mechanically implausible.
The traditional explanation was myofascial release: that pressure physically deforms fascia, breaks up adhesions, and restores tissue to its proper length.
The problem is the force required. Fascia is remarkably strong connective tissue. Estimates of the force needed to produce meaningful plastic deformation in dense fascia are far beyond what a person can generate leaning on a foam cylinder. Body weight on a roller does not come close.
The timing is also wrong. Structural tissue change would persist. The range of motion effect from rolling fades within roughly half an hour, which is the signature of a nervous system effect rather than a structural one.
The better-supported explanation is neurophysiological. Pressure and movement stimulate mechanoreceptors in the skin, muscle, and fascia. That afferent input appears to reduce the nervous system’s protective restriction of range, sometimes described as increasing stretch tolerance. In plain terms, the tissue is not longer, but your nervous system permits more range because it perceives less threat.
There is likely also a global rather than local effect. Studies have found that rolling one limb can increase range in the opposite, untreated limb, which is impossible under a purely mechanical model and entirely consistent with a central nervous system one.
Why this matters practically: if the effect is neural, then pain is not required. Aggressive, teeth-gritting rolling is not more effective than moderate pressure, and there is reason to think excessive pressure is counterproductive because it increases the threat signal rather than reducing it.
How to actually use it before training
The pre-training use case is the strongest one, and the protocol is short.
Duration: 30 to 60 seconds per muscle group is where most of the benefit sits. Studies using longer durations do not consistently show better results, and very long rolling wastes warm-up time.
Pressure: moderate. A useful gauge is a discomfort level around four to six out of ten. Anything that makes you hold your breath or tense the surrounding muscles is too much and is likely working against the mechanism.
Target the areas relevant to the session, not everything. For a squat session, that is typically quadriceps, adductors, glutes, and calves. For an upper body session, thoracic spine, lats, and pecs. Rolling everything before every session is a time cost with no additional benefit.
Move slowly, and pause on tender spots for 20 to 30 seconds rather than rolling rapidly back and forth. Slow movement with brief sustained pressure produces the effect more reliably.
Follow it with active movement. Rolling increases available range; using that range with dynamic movement is what makes it useful for the session ahead. Rolling followed immediately by heavy lifting without any movement in between leaves the benefit on the table.
A reasonable pre-training sequence: three to four minutes of rolling on relevant areas, then five minutes of dynamic movement, then the first working sets. Total warm-up around ten minutes.
What not to do: replace a proper warm-up with rolling. Rolling does not raise tissue temperature, does not elevate heart rate, and does not prepare the nervous system for load in the way that progressive movement does.

How to use it after training and on rest days
The recovery use case is real but more modest, and the protocol differs.
Timing: immediately after training, or in the 24 to 72 hour window when soreness peaks. Both appear to help with perceived soreness, and there is no strong reason to choose one over the other.
Duration: longer is acceptable here, in the range of 60 to 120 seconds per area, because there is no warm-up time budget to protect and the goal is different.
Pressure: lighter than pre-training, particularly on sore tissue. Aggressive rolling on already-sore muscle adds discomfort without evidence of additional benefit.
What to expect: a moderate reduction in how sore you feel, and possibly slightly better performance in a session during that window. Not a dramatic acceleration of recovery, and not a reduction in the actual muscle damage.
On rest days, rolling is a reasonable component of an easy movement session alongside walking, light mobility work, and general activity. The value there is as much about the movement and the routine as about the roller specifically.
An honest note on the placebo and expectation component: a meaningful share of the perceived soreness benefit may come from the ritual, the attention to the body, and the expectation of relief. That does not make it useless. Perceived soreness is a real outcome that affects how you train the next day, and something that reduces it cheaply and safely is worth doing. It does mean you should not build a training plan around foam rolling as a recovery intervention.
Where rolling is the wrong tool
Knowing the limits prevents both wasted time and occasional harm.
For lasting flexibility gains, rolling is not the tool. Range of motion that persists comes from regular stretching, particularly loaded stretching and strength training through a full range. Rolling produces a temporary window; strength work through that range is what makes it permanent.
For the IT band specifically, direct rolling is largely misapplied. The iliotibial band is dense connective tissue firmly attached along the femur, and it is not a muscle that can relax or lengthen under pressure. It is also exquisitely uncomfortable to roll. Where IT band symptoms are present, the more productive targets are usually the tensor fasciae latae, the glutes, and the vastus lateralis, alongside strength work for hip abduction.
For pain in a specific spot that does not resolve, rolling is a delay rather than a treatment. Persistent localized pain warrants assessment rather than more pressure.
Areas to avoid rolling directly: the lower back, where rolling can cause the lumbar spine to hyperextend without the support the thoracic spine has; directly over bony prominences and joints; over the front of the neck; and over any area with a known injury, recent surgery, varicose veins, or reduced sensation.
For the thoracic spine, rolling is appropriate and useful, and it is one of the better applications, particularly for people who sit a lot. Supporting the head and avoiding rolling into the lower back are the key technique points.
This is general information, not medical advice. Anyone with a circulatory condition, a bleeding disorder, osteoporosis, neuropathy, or who is pregnant should check with a clinician before using pressure-based tools, and any sharp, radiating, or numbing sensation is a reason to stop.
What Nobody Tells You About Foam Rollers
Roller density matters less than technique, and softer is a reasonable default. The instinct to buy the firmest, most textured roller available is understandable and usually wrong. If the mechanism is neural, excessive pressure that produces guarding works against the goal. A medium-density smooth roller serves most people better than an aggressive textured one.
Rolling should not require holding your breath. Breath-holding is a reliable sign that you have exceeded useful pressure and triggered a protective response. If you cannot breathe normally, reduce the pressure by supporting more of your body weight with your hands or your opposite leg.
The tender spot is not necessarily the problem. Trigger point theory is far less settled than its popularity suggests, and the reliability of locating trigger points is poor even among trained practitioners. A tender area is worth attention; it is not a diagnosis.
A ball outperforms a roller for small areas. Glutes, pecs, the foot, and the area around the shoulder blade are all better served by a lacrosse or massage ball, which can apply pressure to a specific area that a large cylinder cannot reach.
Rolling before bed can be genuinely useful for people who find it helps them wind down, and the parasympathetic effect of slow pressure and breathing is plausible even if it is not the effect being marketed.
Vibrating rollers show some additional benefit in the research, particularly for range of motion and perceived soreness, though the effect over a standard roller is modest. They are a reasonable upgrade and not a necessary one.
The one that saves the most wasted effort: ten minutes of rolling three times a week does essentially everything rolling can do. Longer, more frequent, and more painful sessions do not scale the benefit, because the mechanism has a ceiling and you reach it quickly. Time beyond that is better spent on strength work through a full range, which is what actually changes tissue capacity.
FAQ: Foam Rolling Questions, Answered
Should it hurt?
No. Moderate discomfort, around four to six out of ten, is the useful range. Pain intense enough to make you tense up or hold your breath is likely counterproductive given how the effect appears to work.
How often should I roll?
Three to five times a week is plenty for most people, either before sessions, after them, or on rest days. Daily is fine and not necessary.
Does rolling before a workout reduce my strength?
The research suggests it does not, which is its main advantage over prolonged static stretching before power or strength work. Range improves without a measurable performance cost.
Can foam rolling replace stretching?
Not for lasting change. Rolling opens a short window of increased range; stretching and full-range strength work are what produce durable flexibility. They are complementary rather than interchangeable.
TL;DR:
- Rolling reliably increases range of motion short term without the strength cost of long static stretching
- It modestly reduces perceived soreness, and it does not break up fascia, adhesions, or scar tissue
- The mechanism appears neural, which means pain is unnecessary and moderate pressure is sufficient
- Use 30 to 60 seconds per area before training followed by movement, longer and lighter after
- Avoid the lower back and direct IT band work, and use strength through full range for lasting flexibility
Cut your rolling pressure to a four out of ten at your next session and add two minutes of dynamic movement after. That combination does more than grinding through it ever did.
Keep Reading
This article is for general informational purposes only and is not medical advice. Always consult a qualified health professional for guidance specific to you.
